Issue #004
Upcoming issue. Topics: complex coronary intervention, intracoronary imaging, structural.
Interventional Cardiology
Clinical Assistant Professor, Case Western Reserve University. Harrington Heart & Vascular Institute, UH Elyria and UH Cleveland Medical Centers.

Interventional Cardiologist
University Hospitals | CWRU School of Medicine
For Patients
A CTO (chronic total occlusion) is a coronary artery that has been 100% blocked for months or years. It is the most difficult blockage to treat with catheters. It is so difficult that many patients are told their only options are bypass surgery or "living with it".
Opening a totally blocked artery requires dedicated wires, intravascular imaging, dual-catheter access, and techniques like the retrograde approach. These skills take years of focused training to master.
Because CTO PCI is the most technically demanding procedure in interventional cardiology, the operators who do it routinely develop a level of precision, planning, and bailout readiness that few others reach.
Calcified lesions, bifurcations, left main disease: the same mastery built on the hardest blockages makes a CTO operator exceptionally prepared for any complex intervention, not just CTOs.
About
I grew up in Northeast Brazil, where patients with complex coronary disease were often told their only options were open-heart surgery or medical therapy alone. That treatment gap shaped my career: I dedicated myself to mastering the most technically demanding forms of coronary intervention.
After fellowship at Instituto Dante Pazzanese de Cardiologia in São Paulo and immersion in the Japanese CTO influence, I returned to Maceió, Alagoas, and built one of Brazil’s highest-volume CTO programs from the ground up.
Many patients were considered “too complex” for catheter-based treatment. This treatment gap profoundly influenced my professional direction.
Now at UH Elyria and UH Cleveland Medical Centers (Harrington Heart & Vascular Institute), appointed Clinical Assistant Professor at Case Western Reserve University School of Medicine. Ohio Certificate of Conceded Eminence (COCE), a licensure reserved for internationally recognized physicians demonstrating extraordinary ability.
Lead Faculty & Program Director of CTO IN ACTION (Boston Scientific). Co-Director of CTO Club Brazil, the largest CTO immersion course in Latin America. Published the OPTEM-oHCM technique in JACC Case Reports, selected for “The Best of JACC” reprint.
Fellowship in hemodynamics and interventional cardiology at a global reference center in cardiovascular interventions and pivotal stent research.
Training in Tokyo and Kobe: structured algorithms, wire escalation, retrograde techniques, imaging-guided strategy. 2nd Prize, TMT Complex Case Competition.
Built a high-volume complex coronary intervention program in Northeast Brazil. 409 consecutive CTO procedures, 90–94% success, >98% survival.
Recruited as Clinical Assistant Professor. Ohio COCE licensure. Expanding CTO, complex PCI, and CHIP capabilities.
Career Timeline
CWRU / University Hospitals, Cleveland, OH
Santa Casa de Maceió, Alagoas, Brazil
Instituto Dante Pazzanese, São Paulo
Instituto Dante Pazzanese, São Paulo
Federal University of Paraíba (UFPB)
Memberships
Official Mandate Holder, International Affairs Committee
Brazilian & Latin American Interventional Cardiology
Council of Cardiovascular Interventions, Vocal Member
Expertise
Chronic total occlusions, bifurcation, left main, calcified lesions, atherectomy, lithotripsy
IVUS/OCT-guided optimization, plaque characterization, stent assessment
Impella, IABP, ECMO, multivessel disease, depressed LVEF, unprotected left main
FFR, iFR, physiological assessment of intermediate lesions
Advanced revascularization, ischemia-guided assessment, multimodal optimization
IVUS-guided procedures in CKD, contrast minimization strategies
DCB strategies, small vessel disease, ISR treatment
CTO IN ACTION Lead Faculty. Co-Director, CTO Club Brazil. International proctor.
Personal Outcomes
| Metric | 2023 (n=110) | 2024 (n=146) | 2025 (n=126) |
|---|---|---|---|
| Technical Success | 94.5% | 93.2% | 92.1% |
| In-Hospital Survival | 98.2% | 93.2% | 99.2% |
| Retrograde Use | 27.0% | 20.6% | 42.9% |
| ADR Use | 9.0% | 8.2% | 4.8% |
Case volumes derived from institutional records and personal procedural logs. Data available upon request.
Case Library
Curated collection of complex CTO and coronary intervention cases shared from the cath lab. Cases originally posted on @evandrofilhobr on X.
 Multivessel CTO
Triple-vessel CTO PCI in a single session. RCA PCI followed by LCx CTO via retrograde ipsilateral OM channel (wire knuckle + antegrade Gladius MG), then LAD functional CTO with antegrade wiring at a bifurcation.
 CTO + Rota
RCA CTO with severe calcification treated with bi-directional approach. Retrograde via septal channels, RCART technique, and rotational atherectomy 1.75mm for lesion modification.
 CTO AWE
LAD CTO tackled with antegrade wire escalation (AWE): Fielder FC followed by Miracle 3 with Finecross MG microcatheter. J-CTO score 1. Straightforward antegrade crossing.
 IVUS 60MHz
High-definition intravascular ultrasound with the 60MHz Altaview catheter. Plaque characterization and stent optimization for CTO post-PCI assessment.
Clinical Pearls
Practical tips and technical pearls from over 1,000 CTO PCI cases. Lessons learned from the catheterization laboratory, shared on X and in live courses.
Begin every CTO with a soft polymer-jacketed wire (Fielder XT-A/R). If no progress within 5 min at the proximal cap, escalate to a tapered stiff wire (Gaia 2nd/3rd). Avoid wasting time with intermediate wires in a hard proximal cap.
When angiography is ambiguous, use IVUS from a side branch related to the proximal cap — when one exists — to define the entry point. This reduces subintimal entry and improves first-pass true lumen crossing rates.
For retrograde access via septals: use a Regular Sion, Sion Black, SUOH 03, AnyReach P 0.3, or Samurai RC with a Corsair/Caravel microcatheter. Navigate the first septal that clearly connects. If it fails, move to the next one quickly. Avoid forcing through a tortuous channel.
In heavily calcified CTOs, never stent without lesion modification. Rotational atherectomy (1.5mm burr), orbital atherectomy, or intravascular lithotripsy (IVL) before stent placement. IVUS confirms adequate expansion.
Plan the full procedure before the first wire enters the CTO: antegrade vs. retrograde, which collateral channels, bailout plan. Set a time/contrast limit and respect it. Failed CTO PCI with preserved collaterals is not a failure.
After CTO recanalization, always run IVUS to confirm true lumen position, size the vessel accurately, and ensure stent expansion >80% of reference area. Underexpansion in long CTO stent segments is the #1 cause of stent thrombosis.
Procedural Vignettes
Selected complex cases shared on @evandrofilhobr. Each card embeds the original post with a brief technical annotation: target lesion, strategy and bailout decisions made in the cathlab.
 View on X
Patient declined surgical revascularization. Single transradial 8F access with EBU 3.5 guide for adequate backup. The case illustrates strategic guide selection and access planning when committing to PCI of a left main bifurcation/trifurcation in the setting of a proximal LAD CTO.
 Watch on X
True bifurcation lesion with extremely difficult side branch access. Streamline Reverse Wire technique used to gain access to the diagonal, followed by IVUS-guided mini-crush stenting. Demonstrates structured wiring strategies and the role of intracoronary imaging for two-stent bifurcation optimization.
 Watch on X
Extensive calcified disease complicated by coronary laceration during the procedure. Bailout managed with Ping-Pong dual-guide technique to maintain wire position for both balloon tamponade and covered stent delivery, with definitive sealing using a Papyrus covered stent. Worth reviewing for any operator dealing with complex calcium and perforation preparedness.
 Watch on X
Patient with prior SAVR (mechanical prosthesis, 20-year history) presenting with acute dyspnea, cardiogenic shock (BP 80/40) and new LBBB on ECG. Referred for emergent catheterization. Vignette highlights the diagnostic challenge of suspected mechanical valve dysfunction versus acute coronary syndrome in a hemodynamically unstable patient.
Conferences & Lectures
Regular participant, faculty, and invited speaker at multiple national and international interventional cardiology conferences since 2014.
Speaker & Panelist (2019–2024)
Invited speaker and panelist at the Latin American Society of Interventional Cardiology joint congresses with SBHCI. Topics in CTO PCI, complex coronary interventions, and intravascular imaging.
Complex Case Competition
TMT Winter Program (Complex PCI / CTO Techniques), awarded 2nd Prize in Complex Case Competition
International Faculty Operator
Live case transmission from Santa Casa de Maceió at the Puerto Rico Society of Interventional Cardiology Meeting
Co-Director & Live Case Operator (2022–2025)
Co-Director since the 2nd edition. Largest CTO immersion course in Latin America: 120+ attendees, 19 states, international faculty. Live complex CTO cases with real-time educational discussion.
Faculty, Speaker, Moderator (2014–2025)
Annual participation as faculty at Brazil's national interventional cardiology congress
Abstract Presentations (2014, 2025)
Presented research on OCT reproducibility, DCB in ISR, and CTO outcomes at TCT
Scientific Output
Peer-reviewed publications in high-impact journals, co-authored consensus documents, and ongoing research in interventional cardiology.
Catheterization and Cardiovascular Interventions
Catheterization and Cardiovascular Interventions · Review
Journal of Interventional Cardiology · Review · Open Access
Journal of Interventional Cardiology · Review · Open Access
JACC: Case Reports
JACC: Case Reports
Cardiovascular Revascularization Medicine: Interesting Cases · 13:100169
The American Journal of Cardiology · 274:12–20
Cardiovascular Revascularization Medicine
Coronary Artery Disease
Cardiovascular Revascularization Medicine
Catheter Cardiovasc Interv · 106(7):3444–3455
GE HealthCare White Paper
Curated CTO Literature
Biweekly critical appraisal of high-impact papers in chronic total occlusion PCI, complex coronary intervention and intracoronary imaging. Each issue: TL;DR, methods, key results, critical appraisal and a take-home for the cathlab.
Wu and the APCTO Club propose ZOLUTION, a simplified antegrade 3D wiring technique that drops the need for a mental 3D image and 90 degree apart views. Critical appraisal of methods, claims, limitations, and the practical take-home for the cathlab.
The first placebo-controlled trial of CTO PCI. Khan, Al-Lamee, Davies et al. randomized 50 patients to CTO PCI vs sham procedure with auditory isolation blinding. OR 4.38 (95% CrI 1.57–12.69), Pr[Benefit] = 99.6%, +30.6 angina-free days at 6 months. Critical appraisal of design, Bayesian methodology, and what it means for patient selection.
556 patients with complex bifurcations randomized to IVUS-guided vs angiography-guided DK crush. TVF 6.1% vs 14.7% (HR 0.40; 95% CI 0.23–0.71) — the largest imaging-guidance effect in any complex PCI trial. Why the effect is so big, and the practical IVUS protocol for two-stent bifurcations.
Upcoming issue. Topics: complex coronary intervention, intracoronary imaging, structural.
New Series
3–5 papers per week. Brief summary + clinical take. CTO PCI, complex intervention, intracoronary imaging.
@evandrofilhobr on X
Selected as official Social Media Ambassador for leading international interventional cardiology congresses, responsible for real-time digital coverage, case dissemination, and educational content amplification.
Patient & Physician Resource
Plaque buildup narrows the arteries that supply blood to the heart, causing chest pain, shortness of breath, and reduced quality of life. Understanding the disease is the first step toward effective treatment.
When a coronary artery becomes 100% blocked, patients often suffer refractory angina and exercise limitation. Many are told nothing more can be done, but modern CTO PCI techniques achieve success rates above 85%.
For patients with left main disease, severe calcification, or multivessel involvement who face high surgical risk, advanced percutaneous techniques with imaging guidance and mechanical support offer a viable alternative to open-heart surgery.
Whether you are a patient seeking relief from angina that medications cannot control, or a physician looking for a CTO and complex PCI specialist to discuss a challenging case, I am here to help.
Clinical Practice
Coronary angiography, left heart catheterization, hemodynamic assessment, and vascular access management
CTO revascularization, bifurcation PCI, left main disease, calcified lesions with atherectomy/lithotripsy
IVUS and OCT-guided PCI optimization, plaque morphology analysis, stent expansion assessment
TAVI, MitraClip, left atrial appendage closure, ASD/VSD/PDA closure procedures
FFR and iFR assessment for intermediate lesions, physiological guidance for revascularization
Second opinions, complex case review, multidisciplinary heart team collaboration
Industry Proctorships · 2019–June 2026
Lead proctor for complex CTO-PCI across Brazil through partnerships with Boston Scientific and other industry partners. Over 300 live proctoring cases in 45+ cities spanning all five macro-regions, teaching AWE and ADR approaches with advanced IVUS/OCT guidance.
Part of the University Hospitals system in Northeast Ohio.
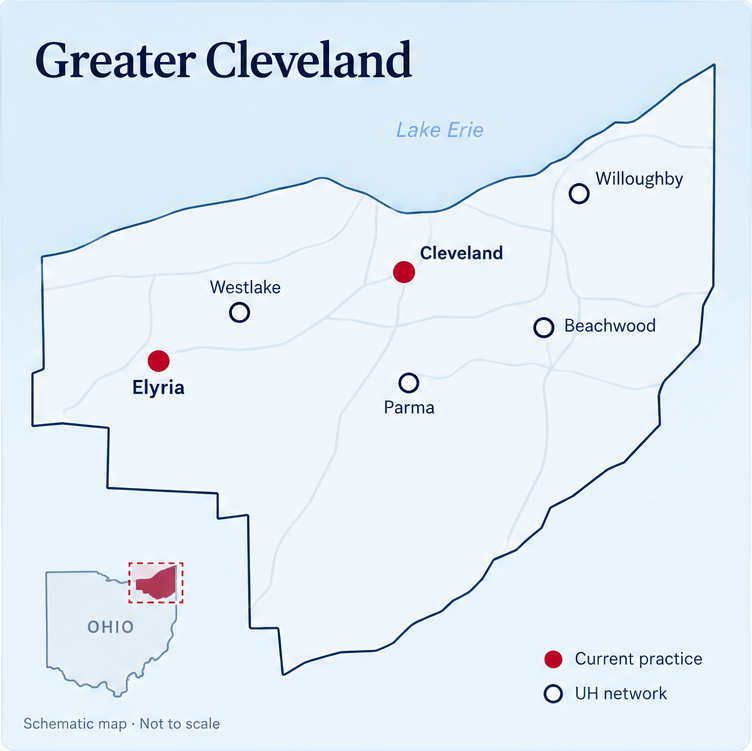
Cleveland, OH
Harrington Heart & Vascular Institute
Elyria, OH
Primary officeBeachwood, OH
Willoughby, OH
Parma, OH
Westlake, OH
Get in Touch
UH Elyria Medical Center · Harrington Heart & Vascular Institute
125 E Broad St, Elyria, OH 44035
UH Cleveland Medical Center · Harrington Heart & Vascular Institute
11100 Euclid Ave, Cleveland, OH 44106
Case Western Reserve University School of Medicine